
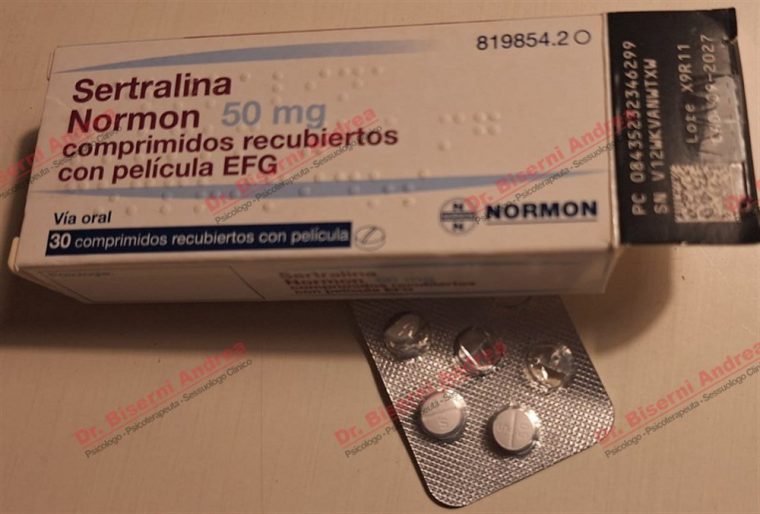
$29.60
Sertraline for premature ejaculation, taken daily or before sex
- sertraline
- Film-coated tablet
- 25mg, 50mg, 100mg
- Prescription only
Taking sertraline for premature ejaculation means choosing between two schedules that behave nothing like each other. Daily dosing builds a steady serotonin effect over two to three weeks and delays ejaculation whether or not sex is planned. A single dose four to eight hours beforehand works faster but less powerfully, and the difference between the two is large enough that picking the wrong one is the usual reason a man decides the drug "did not work". Sertraline 50 mg is the dose most men end up on either way, and it is prescribed off-label for this: the licence covers depression, obsessive-compulsive disorder, panic, PTSD and PMDD, not ejaculation.
What the delay actually measures
Trials in this area measure intravaginal ejaculatory latency time, stopwatch-timed by the partner. The baseline in lifelong premature ejaculation is usually under a minute. Daily SSRIs multiply that figure rather than adding a fixed number of seconds, which is why the starting point matters: a four-fold increase on a thirty-second baseline is two minutes, and on a two-minute baseline it is eight.
In the comparative work on daily dosing, sertraline sits in the middle of the class — a roughly four-fold increase in latency, behind paroxetine and ahead of fluoxetine. On-demand use produces something closer to a doubling. Neither figure is a promise for an individual; they are averages across groups, and the spread inside those groups is wide.
The dose ladder, and where to stop
Daily treatment starts at 25 mg for the first week, mostly to find out how the nausea goes, then 50 mg. If latency has not moved after three weeks at 50 mg, 100 mg is a reasonable step. Above 100 mg the ejaculatory benefit flattens while the sexual side effects — reduced desire, difficulty reaching orgasm at all — keep climbing, so 200 mg is a dose for psychiatric indications, not for this one.
On-demand dosing is 50 mg taken four to eight hours before sex, which demands a level of planning most couples find harder than a daily tablet. It is the better fit when sex is infrequent, or when a man wants to keep the drug out of his system the rest of the week. The two approaches can be combined — a low daily dose with a top-up before a planned occasion — but that is a prescriber's decision, not a self-management trick, because the total daily ceiling still applies.
Prices by strength and pack
Indicative prices in US dollars. Thirty tablets is one month of daily treatment, so the larger packs are where the per-day cost drops meaningfully — worth knowing before anyone decides to buy sertraline online in the smallest box available.
| Pack | 25 mg | 50 mg | 100 mg |
|---|---|---|---|
| 30 tablets | $29.60 | $32.10 | $38.40 |
| 60 tablets | $49.80 | $54.60 | $65.20 |
| 90 tablets | $67.20 | $73.80 | $88.50 |
| 120 tablets | $81.40 | $89.70 | $107.80 |
| 180 tablets | $108.90 | $120.60 | $145.30 |
| 270 tablets | $145.20 | $161.40 | $194.70 |
The side effect that is the point, and the ones that are not
Delayed ejaculation is the therapeutic effect here, and it does not come on its own. Nausea in the first fortnight is the commonest complaint and usually settles; taking the tablet with food helps more than halving the dose. Sweating, dry mouth and either drowsiness or early-morning waking are frequent. Reduced libido and blunted orgasm are the two that make men stop, and they are dose-related: a man who gains four minutes but loses interest in sex has not gained anything.
Stopping abruptly after weeks of daily use produces dizziness, electric-shock sensations and irritability. Sertraline's half-life is around twenty-six hours, long enough that the effect is milder than with paroxetine but real, so a taper over two to four weeks is the normal way out.
What must not be combined with it
Monoamine oxidase inhibitors are an absolute contraindication, with a fourteen-day gap in either direction; the same applies to linezolid and intravenous methylene blue. Pimozide is out. Triptans, tramadol, lithium, St John's wort and any second serotonergic drug raise the risk of serotonin syndrome, which in practice means telling a prescriber about migraine medication and painkillers rather than only about "real" prescriptions.
NSAIDs, aspirin and anticoagulants increase bleeding risk when added to an SSRI. The dapoxetine stocked in the men's health range is itself an SSRI, so the two are alternatives rather than partners, and the same goes for the combination tablets that contain it — super kamagra and tadapox both carry a dapoxetine dose that should not be stacked on top of a daily SSRI.
When this is the wrong drug
Three patterns point away from a tablet. Ejaculation that became rapid recently, in a man who previously had no problem, is acquired premature ejaculation, and the cause is often thyroid disease, prostatitis or an erection problem the man is racing to finish before it fades — treat the cause and the latency returns. Rapid ejaculation that only happens with one partner, or only in particular circumstances, is situational and responds to the clinical work rather than to serotonin. And a man whose real complaint is anxiety about performance will find that the drug lengthens the act without touching the dread around it.
That third pattern is the common one. Where it fits, medication and clinical sexology are not competing options: the tablet buys time while the stop-start and squeeze techniques are learned, and the relapse rate after stopping is lower when both have been done. At this studio the first consultation costs nothing, which makes the question cheap to settle. The rest of the daily-dose options sit in the antidepressants section.
Zoloft generic and what generic changes here
The originator is Zoloft. Zoloft generic preparations contain sertraline hydrochloride at the same strengths and are held to bioequivalence standards, so the pharmacology is the same and the tablet markings are not. For an off-label indication measured in seconds of latency, there is no argument that the originator performs differently; what differs is the price per month.
Where a daily tablet is unacceptable in principle, the alternatives are the on-demand molecules: dapoxetine, which was designed for this single job, and clomipramine at a low pre-planned dose. Where the problem is erection as well as timing, treating the erection first is usually the better order, because men frequently rush to ejaculate while they still can.
Questions people actually ask
How long before I know whether it works?
On a daily dose, judge it at three weeks, not at three days. Some delay appears in the first week, but the full effect builds with steady-state blood levels, and stopping on day four because nothing has changed is stopping before the drug has started.
Can I take it only on the days I need it?
Yes, at 50 mg four to eight hours ahead, accepting a smaller effect. What does not work is taking a daily tablet two or three times a week: that produces neither steady state nor correct timing.
Will it affect my erections?
Not directly — it is not a vascular drug. Indirectly it can, because reduced desire makes arousal harder to reach. If erections were already borderline, that interaction is the thing to watch.
Is it safe to use long term for this?
Men do stay on it for months or years, and the monitoring is unremarkable in a healthy man. The honest caveat is that the evidence base for long-term off-label use is thinner than for depression, and nobody has shown that the latency gain persists after the drug is withdrawn without behavioural work alongside it.
The label these figures come from
Dosing, interaction intervals and adverse-effect frequencies follow the FDA prescribing information for sertraline. The definitions of lifelong and acquired premature ejaculation and the place of daily SSRIs in treatment follow the International Society for Sexual Medicine guidance. This page is information, not a prescription, and the off-label use described here needs a prescriber who knows your history.
Related medicines


Where the facts about Sertraline come from
Sertraline: the strengths, the dosing, what the film-coated tablet form changes, the contraindications and the interaction warnings set out above are the ones in the approved labelling for sertraline — the current FDA label in DailyMed — read against the European product information where this molecule is licensed in the EU. Where a figure here differs from the one in your own pack insert, the insert for the pack you hold is the document to follow.
Sertraline touches mood, sleep and the sexual side effects that decide whether an antidepressant is kept, and that part of the page was read before publication by Dr. Andrea Biserni, psychologist, psychotherapist and clinical sexologist, Ordine degli Psicologi della Toscana n. 3572 sez. A (verify in the national register). The milligrams were not: he is not a prescriber, and the dosing and safety wording for sertraline stays as the regulator wrote it.
How ordering works
Packs of Sertraline run from $29.60 to $194.70. The figure covers the medicine, the pharmacist check and tracked delivery; customs charges raised at the destination are not. Dispatch and tracking are set out under shipping and delivery, what can and cannot come back under returns and refunds, and the contract itself in the terms of sale.
Prices quoted for Sertraline are indicative; the amount charged is confirmed in writing before any payment is taken. As a prescription-only medicine it is never dispatched without a valid prescription from a licensed prescriber — send it through the prescription service and a pharmacist checks it against the strength and quantity before release. Nothing here replaces advice from your own doctor or pharmacist about sertraline, and the studio does not diagnose or prescribe by e-mail.